
Anyone who knows me knows two things: I have lived outside the United States as both a child and an adult, and I love to travel.

The most relevant part of my story is that I received an isolated intestinal transplant in December 2022. About a year and a half later, I took my first international trip post-transplant.
I do not remember much about the three years leading up to my transplant, but my parents promised to take me anywhere in the world WHEN – not if, as I would pragmatically say – I felt better. That is how we ended up spending two weeks in England on what I cleverly named my “Thanks-for-Not-Dying Trip,” like a reverse Make-A-Wish. Surprisingly, my parents were not nearly as amused by the name as I was.
We spent time in Stratford-upon-Avon, Shakespeare’s birthplace, followed by a week in the Lake District, where Beatrix Potter lived and created her children’s books. Did I mention that I am a bit of a nerd?
It was the perfect first trip. I had visited Stratford before, so it felt familiar, and neither destination was too busy or overwhelming. Before my transplant, I was only awake for a few hours each day. Although I now have much more energy, I still need daily naps, and this trip gave me the flexibility to rest.
This summer, three and a half years after my transplant, we took another two-week trip, this time to Scandinavia. The first part was a cruise beginning in Norway and ending in Amsterdam, where we stayed for several additional days.
Before anyone questions the wisdom of an immunocompromised transplant recipient going on a cruise, believe me, I had the same concerns. Cruise ships are known for outbreaks of illnesses such as norovirus, and buffets can present additional food-safety risks. Add thousands of people sharing one space, and there is plenty for any traveler, especially a transplant recipient, to consider.
We selected our cruise carefully. It was adults-only, carried fewer than 1,000 guests, emphasized restaurants rather than buffets, and had three physicians and five nurses onboard. The cruise line also accommodated my medical needs with refrigerator space for my fluids, extra pillows so I could sleep at an incline, reserved seating during bus rides, and plenty of ginger ale.
Normally, my dad plans our trips, and he is excellent at it, but this time we worked with a travel agent who arranged both the cruise and our flights. This helped reduce potential complications from delays, cancellations, or unexpected medical issues. My dad also contacted the airline, TSA, and cruise company so we knew what to expect.

Here are some of the lessons we learned.
Ask for the help you need
The airline can note that you have a disability and may require accommodations. You do not necessarily need to disclose your diagnosis.
Wheelchair assistance or an airport cart can make long terminals, security lines, and connections far less exhausting. Early boarding also gives you additional time to settle in and safely store your carry-on items.
I used a Hidden Disabilities sunflower lanyard during both of my international trips. More than 350 airports participate in the program, and some offer sunflower lanyards, sensory rooms, and quiet spaces.
Plan carefully for medications and supplies
All of my medications stayed with me in my carry-on luggage. I brought more than I needed for the scheduled length of the trip in case we experienced a canceled flight, an unexpected hospital admission, or another delay.

Research the medication laws of every country you plan to visit. A medication that is legal with a prescription at home may be restricted elsewhere. Keep medications properly labeled and carry copies of your medication list and letters from your medical providers.
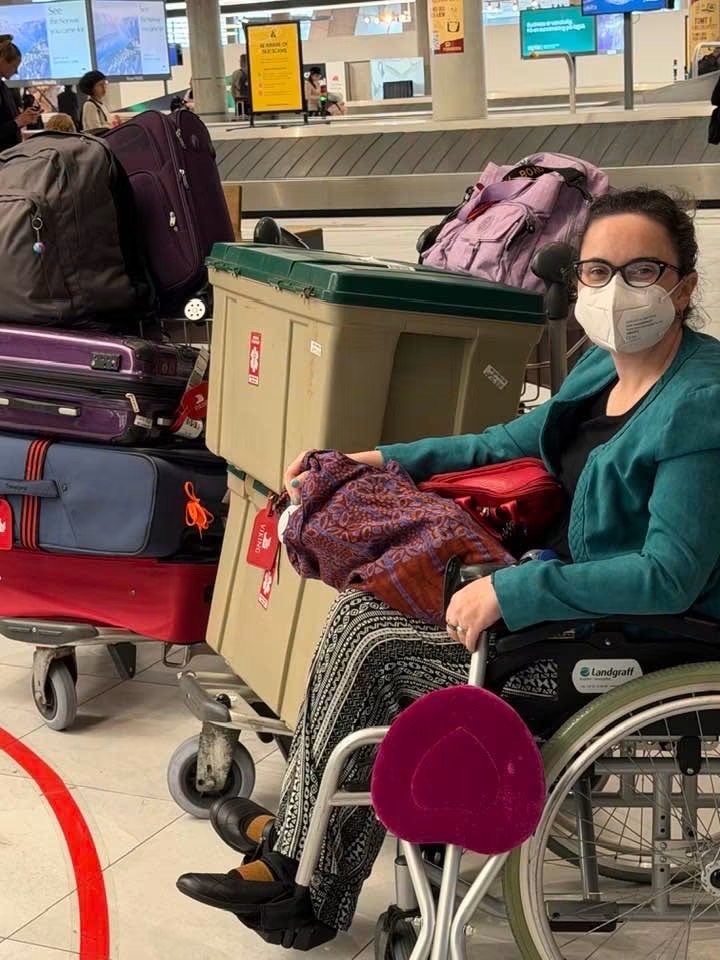
My medical needs are unusually complex. I run three liters of IV fluids each day, and the bags must remain cool because they are customized according to my weekly laboratory results. I traveled with more than 150 pounds of supplies packed into two large trunks. Each trunk contained a detailed inventory, along with letters from my physician and infusion pharmacist.
Airline policies for medical equipment and baggage vary, so contact the airline well in advance and ask what documentation, weight limits, or special arrangements may apply.
I also carried an extra infusion pump, electrolyte packets recommended by my medical team, snacks for low blood sugar, an extra change of clothes, hand sanitizer, disinfecting wipes, masks, and a foldable cane.
My days of traveling light may be over, but my days of traveling are not.
Expect additional screening

During my first post-transplant trip, I still had feeding tubes, an ileostomy, a central line, and plenty of scars. When I was selected for a pat-down, I requested that it be done privately. It was no big deal. I have been through much worse.
On our return from this most recent trip, customs officers questioned us several times about our medical trunks. Once they saw me waiting in a wheelchair and understood what the luggage contained, we were able to continue without a problem.
Patience, documentation, and a sense of humor go a long way.
My three biggest pieces of advice
1. Communicate.
Speak with your transplant and medical teams well before your trip. This is not necessarily about asking permission. It is about learning how to travel as wisely and safely as possible.

Ask whether your destination is medically appropriate, what to do during an emergency, and where you should seek care if something happens. Review your medications early enough to arrange any necessary refills.
You should also seriously consider travel insurance. Read the policy carefully so you understand what is covered, including cancellations, medical treatment outside your home country, and emergency evacuation. Be prepared for the possibility that you may need to pay for care upfront, even with insurance.
2. Plan, plan, PLAN.
Several months before our trip, I began a running list of questions, supplies, and tasks.
Request a letter from at least one of your medical providers that includes your name, the provider’s contact information and license number, confirmation that you are under their care, and an explanation of why you need your medications or medical supplies.
Research the entry requirements, medication restrictions, electrical outlets, weather, accessibility options, and healthcare resources for each destination. The more you know before leaving, the easier it will be to handle the unexpected.

I would rather be overly prepared than discover thousands of miles from home that I forgot something important. I should have been a Girl Scout.
3. As much as possible, go with the flow.
Even with careful planning, something unexpected will probably happen. Arrive at the airport earlier than you think you need to. Give yourself time to rest, ask for assistance, and adjust when plans change.
Most importantly, have fun. Allow yourself to experience something new, or something you once loved and thought you had lost. Take the chances. Make memories. JUST LIVE!

Now that my family and I have learned how to manage international travel with all my medical needs, I keep telling my parents we have to keep traveling. It would be a waste of all that work not to do it again, right?
My experience is specific to my transplant and medical conditions, but I hope it gives other transplant recipients a helpful starting point. Whether you are an experienced traveler or planning your first post-transplant trip, work with your medical team, prepare carefully, and remember why you are going.
Making memories for yourself and with the people you love is one of life’s greatest gifts, right alongside the ultimate gift of “not dying.”

Recently, I found myself in the emergency room battling a serious infection. When my symptoms first appeared, I wondered if I might be dehydrated, so I paid closer attention to my fluid intake. But as the pain and fatigue increased, I knew I needed medical attention. Like many transplant recipients, one of my first concerns was what the infection and possible dehydration could mean for my newly transplanted kidney.
One of the instructions I received was to stay hydrated, but not only with water. My care team also recommended electrolyte drinks such as Gatorade or Pedialyte. That made me realize that although we hear a lot about hydration, we may not always understand the difference between replacing water and replacing electrolytes.
Why hydration matters after transplant
Water helps our bodies circulate blood, regulate temperature, remove waste, and maintain the right balance of minerals. Significant dehydration can lower blood pressure and reduce blood flow to the kidneys, potentially causing acute kidney injury and placing added stress on a transplanted kidney. The National Kidney Foundation notes that severe dehydration can quickly damage kidneys.

However, more is not always better. Some people need to limit fluid intake because of reduced kidney function, heart problems, swelling, or other medical conditions. Fluid needs can also change with hot weather, exercise, illness, and certain medications, so transplant recipients should follow the daily fluid goal recommended by their care team.
What are electrolytes?
Electrolytes are minerals, including sodium, potassium and magnesium, that help regulate fluid balance, muscle function, nerve signals and heart rhythm. We normally obtain them through food and beverages, while our kidneys help keep their levels balanced. When we lose fluids through heavy sweating, fever, vomiting or diarrhea, we may lose electrolytes along with water. This is why water alone may not always be enough during certain illnesses or periods of significant fluid loss.
But electrolytes are not automatically beneficial just because they are marketed as healthy. Too much or too little sodium, potassium, or magnesium can cause problems. This is particularly important for transplant recipients whose kidney function, medications and laboratory values can affect how these minerals are processed.

When water is generally enough
For routine daily hydration, including meals, errands, walks and light or moderate exercise without heavy sweating, water is usually the best place to start. If you are eating normally and not losing a significant amount of fluid through sweat or illness, your meals will generally provide the electrolytes you need. Carrying a water bottle, drinking regularly, and following the fluid goal set by your transplant team can make hydration easier to manage.
When an electrolyte drink may be helpful
Electrolyte drinks may be helpful during vomiting, diarrhea, fever, heavy sweating, prolonged activity in hot weather, or an illness that makes it difficult to eat and drink normally.
This was the situation I encountered. Because I was fighting an infection and unable to eat and drink as I normally would, my medical team wanted me to replace more than water alone.

Sports drinks and oral rehydration solutions are not the same. Sports drinks are generally designed to replace some fluid, carbohydrates, and electrolytes lost during exercise. Oral rehydration solutions, such as Pedialyte, use a more specific combination of glucose and electrolytes intended to help the body absorb fluid during illnesses involving vomiting or diarrhea.
The National Institute of Diabetes and Digestive and Kidney Diseases recommends replacing both fluids and electrolytes during diarrhea. It also advises people with weakened immune systems, kidney disease, diabetes, or other health conditions to ask a clinician which product and amount are appropriate.
For transplant recipients, this is not something we should have to guess about. A quick call to the transplant team can help determine whether water, an electrolyte drink or medical evaluation is most appropriate.
Not all electrolyte drinks are the same
The electrolyte beverage aisle has grown enormously. There are sports drinks, powders, tablets and enhanced waters marketed for energy, recovery or wellness. Their ingredients can vary widely.
Before choosing one, look at:
- Sodium: It helps replace sodium lost through sweat, vomiting or diarrhea, but some products contain more than you may need.
- Potassium: Products containing large amounts may not be appropriate for someone with elevated potassium or reduced kidney function.
- Sugar: Glucose helps the body absorb water and sodium in a properly formulated oral rehydration solution, but that does not mean every sugary beverage is helpful.
- Added ingredients: Caffeine, herbal blends, stimulants, and unfamiliar supplements should be reviewed with the transplant team or pharmacist because they may not be appropriate or could interact with medications.
A label that says “electrolytes” does not necessarily mean the product is right for your current needs. The appropriate drink may depend on your kidney function, blood pressure, blood sugar, laboratory results, and medications.
My biggest takeaway: listen to your body
Water remains my everyday choice. Electrolyte drinks may have a role when I am losing both fluids and minerals or when my medical team recommends one. But no amount of water or electrolytes could have treated my underlying infection. When my pain and fatigue continued to increase, I needed medical attention.
We work so hard to care for our transplanted organs. Staying hydrated is part of that responsibility, but so is listening to our bodies, recognizing when something has changed, and knowing when it is time to ask for help.
| Important note: This article reflects my personal experience and is intended for general education. It should not replace guidance from your transplant team. Ask your care team about your individual fluid and electrolyte needs, especially during illness or extreme heat. |
Sources referenced
National Kidney Foundation: Can Dehydration Affect Your Kidneys?
National Institute of Diabetes and Digestive and Kidney Diseases: Treatment of Diarrhea
Over the past week, I had the opportunity to be part of two experiences within the transplant community that, while different in setting, were deeply connected in purpose. Whether standing in a busy exhibit hall or speaking to clinicians and researchers, one thing became clear: connection and advocacy build upon one another.
Connection creates the space for stories to be shared, and advocacy ensures those stories are heard.
Where Connection Begins
On June 18th, I traveled to Denver for the Transplant Games of America, where I represented the TransplantLyfe community alongside my friend and colleague LaVise. From the very first day in the TGA Village, we were completely overwhelmed in the best possible way.
Patients, care partners, and family members continuously stopped by and shared their stories. Each interaction reinforced how powerful it is to simply listen.
I spoke with a woman who received her transplant in 1994 and has been coming to the Games for decades. When we talked about TransplantLyfe, she shared how meaningful it was to see something like this exist now. At the time of her transplant, there were no resources to connect, so she spent years building support groups herself. During our conversation, I could tell she had done so much for this community, as many people stopped by to give her a hug or a friendly pat on the back. I knew I was in the presence of someone who has made a lasting impact.
We also invited people to take a short survey about side effects, and so many were eager to participate. One man immediately stepped up and said, “Oh boy, do I,” joking about whether we’d have enough room to capture them all. There was humor in those moments, but also a deeper truth: side effects are a constant and often invisible part of daily life.
Those conversations stayed with me, especially knowing I would soon be speaking about these same challenges in a clinical setting.
Just before we wrapped up our first day, one attendee said: “Thank you for being here listening and for all the work that you do.” It was simple, but it underscored how meaningful it is to create space for people to feel heard.

Where Connection Becomes Advocacy
That sense of connection carried into my experience speaking at the American Transplant Congress on the hidden burden of transplant success.
Over the past nine years with my kidney transplant, I’ve come to understand that survival is only part of the story. As I sat on that stage, I wasn’t just sharing my own experience, I was carrying the voices and honesty I had just witnessed days before.
When it came time to speak, I shared my journey, including receiving a kidney from my mom, who gave me life not once, but twice. I spoke openly about living with side effects, tremors, additional medications, headaches, gastrointestinal issues, brain fog, and the uncertainty about the future.
As I looked out at the room, I felt encouraged by the willingness to listen. There was openness from clinicians about the burden patients carry and the need for better solutions.
One quote that stayed with me was: “Change is difficult, not changing is fatal.”
It reinforced how important it is to bring patient experiences into these conversations, because the stories shared in community spaces are the same ones that can shape the future of care. After the session, several practitioners came up to thank me for sharing my story. As patients, we often express gratitude; to have that gratitude reflected back was something I will never forget.
Connection and Advocacy, Together
Looking back, what stands out most is how these experiences come together.
The conversations in community spaces are not separate from those happening in clinical settings – they are the foundation.
Connection is where stories begin and advocacy is how those stories create change.
This week reinforced that when we listen, share, and carry those experiences forward, we create the potential for something bigger, not just for ourselves, but for the entire transplant community.

April is Donate Life Month, and it also marks the anniversary of my own Gift of Life on April 20, 2015. Throughout the month, communities come together to honor organ donors whose generosity makes second chances possible. It is a time to reflect on the incredible impact of these donor heroes and to express deep gratitude to their families, as well as the medical teams, hospital staff, and loved ones who support transplant recipients. Truly, it takes far more than a village to make organ donation and transplantation possible.
A few days ago, I experienced something incredibly unique and deeply emotional that I feel compelled to share. I had the honor of attending an Honor Walk at a hospital, held at the request of a family to recognize their loved one who had passed. For privacy, I will refer to her as “T.” She was someone I knew well, a true transplant warrior who had received the gift of a heart and lungs a few years ago. Sadly, she had recently been hospitalized with an infection that could not be managed.

Her family and close friends, including myself and a few fellow transplant recipients, gathered in her room around her bed. Prayers were shared, memories were spoken, and we each had the chance to say our goodbyes. T had made the decision to be an organ donor and had clearly communicated those wishes to her family. Because of that, and with their full support, members of the Organ Procurement Organization (OPO) were present to help coordinate the process and provide support during such a difficult time.
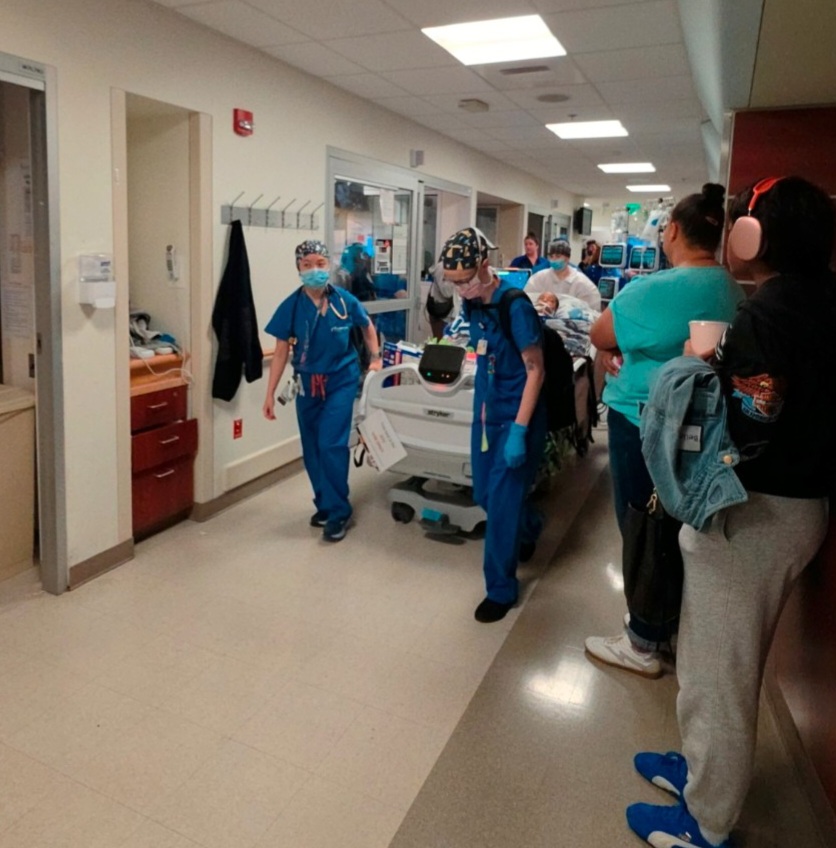
It was finally time. The hospital bed was prepared for transport to the operating room. Moments earlier, an announcement had been made over the hospital’s PA system, inviting all available staff to assemble outside T’s room for the Honor Walk.
The bed, surrounded by family, was gently pushed down a long corridor. On both sides of the hallway, people stood shoulder to shoulder, doctors, nurses, technicians, cleaning crews, security personnel, and loved ones. We were all there to honor and say goodbye to a potential organ donor, someone whose final act could give others the chance to live. As we moved down the hallway, music played softly from a Bluetooth speaker, Stevie Wonder’s “Isn’t She Lovely.”
Once inside the operating room, a clinical team from the OPO became involved in the recovery of any viable organs after it was confirmed that she had passed.
On our way out of the hospital, we saw an SUV from the OPO ready to transport recovered organs to the next recipient.
The following day, we learned that T’s liver had been recovered and transported to a hospital about 300 miles away in New York. I remember visiting her a few years ago while she was waiting for her heart and lungs. She even joined my virtual support group from her hospital room. After a long wait, she finally received “the call” and was transplanted.
Then, just the other day, someone else received “the call” for a liver that would allow them to live, all because T had said “Yes” to organ, eye, and tissue donation. That is what I call the full circle of life. While T may not be here physically, she lives on. Truly,
Organ Donation + Transplantation = Miracles 💯.
Experiences like this are why awareness and education during Donate Life Month matter so much.
During April, many transplant centers and hospitals host Flag Raising Ceremonies to honor and remember organ donors. These brief ceremonies bring together hospital leadership and OPO teams to reflect, express gratitude, and celebrate recipients whose lives have been saved. Often, recipients, living donors, and donor families share parts of their journey.
This April, I have been fortunate to speak at over 10 of these events. I share a small part of my story, focusing on gratitude and what transplant has meant to me over the past 11 years, while also highlighting the ongoing need for organ donation.
I hope to inspire those on their own transplant journeys and encourage everyone to consider organ donation. You can become a Donate Life Ambassador through your local Organ Procurement Organization (OPO) and you can find your local OPO by visiting “Find your OPO.”

My best wishes to all those who are waiting for a life-saving transplant. Your perfect gifts will become available at the right time. In the meantime, please try to stay positive and take care of yourselves so you can be in the best possible mental and physical state, allowing for a smoother transplant journey and healing with the best outcomes.
To my fellow recipients, let us continue to stay compliant, look after ourselves, and take care of the precious gifts of life we have been fortunate to receive, while living our lives as fully as possible.
To those who are not yet registered as organ, eye, and tissue donors, I encourage you to consider doing so. At the very least, have a conversation with your loved ones and make your wishes known.
To register as an organ, eye, and tissue donor, please visit: https://www.organdonor.gov/sign-up/how

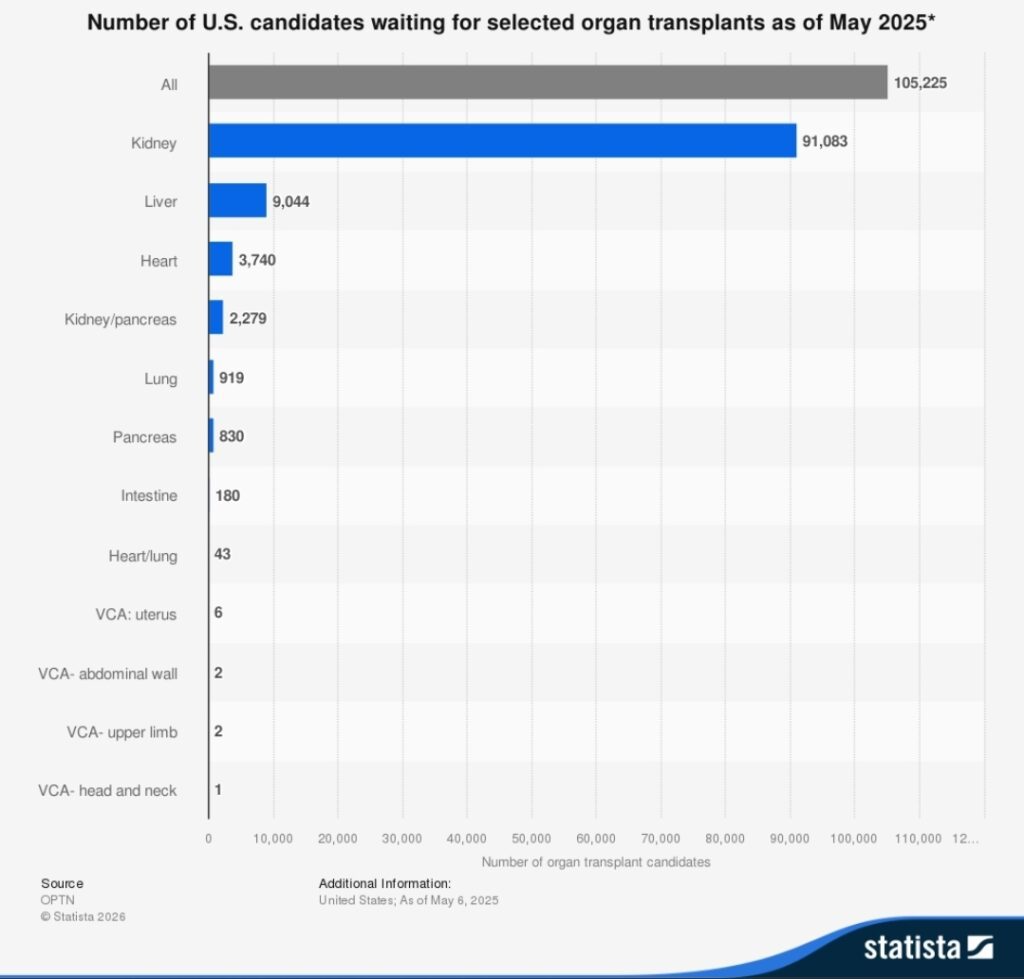
The proposed Living Donor Protection Act (LDPA) of 2025 (S.1552 / H.R.4583) is bipartisan federal legislation introduced in 2025 to protect living organ donors. Protections like the LDPA are essential to helping reduce the national transplant waiting list, which currently includes more than 100,000 individuals. Such legislation may encourage more people to consider becoming living organ donors for those in need of life-saving kidney and liver transplants.
Key Aspects of This Legislation
Insurance Protections:
Once enacted, insurance companies would be prohibited from discriminating against living organ donors—this includes denying coverage, limiting coverage, or charging higher premiums simply because someone is a donor.
Job Security:
When the law is (hopefully) in effect, recovery from organ donation surgery would be covered under the Family and Medical Leave Act (FMLA). This means donors will be able to take unpaid leave while recovering, with job protection to ensure they can return to work.
Status and Next Steps
Current (Federal*) Status:
on February 26, 2026, the LDPA advanced through the Senate Committee on Health, Education, Labor, and Pensions (HELP), moving it one step closer to becoming federal law.
On March 11, 2026, the LDPA was reported to the full Senate.
Next, the legislation will be debated on the Senate floor, followed by a final vote after any amendments are addressed. If approved by the full Senate, it must be reconciled with the House version before being sent to the President, who will either sign it into law or veto it.
Call to Action
We can all reach out to our representatives to ensure that LPDA becomes law. Our voices matter. Every day, people die while waiting for a life-saving transplant.
*There are also state-level laws that provide protections for living organ donors.

When I was 18 years old, I started having strange symptoms: body aches that never went away, a really hard time breathing, and a heart that would skip beats or feel like it was pounding so hard that it would move my entire body. After several misdiagnoses, I was finally diagnosed with end-stage heart failure from a rare genetic condition called left ventricular noncompaction cardiomyopathy. I needed emergency surgery that night to place an Impella to help my heart pump, but it failed. I was placed on another form of life support called ECMO, which would circulate my blood for me.
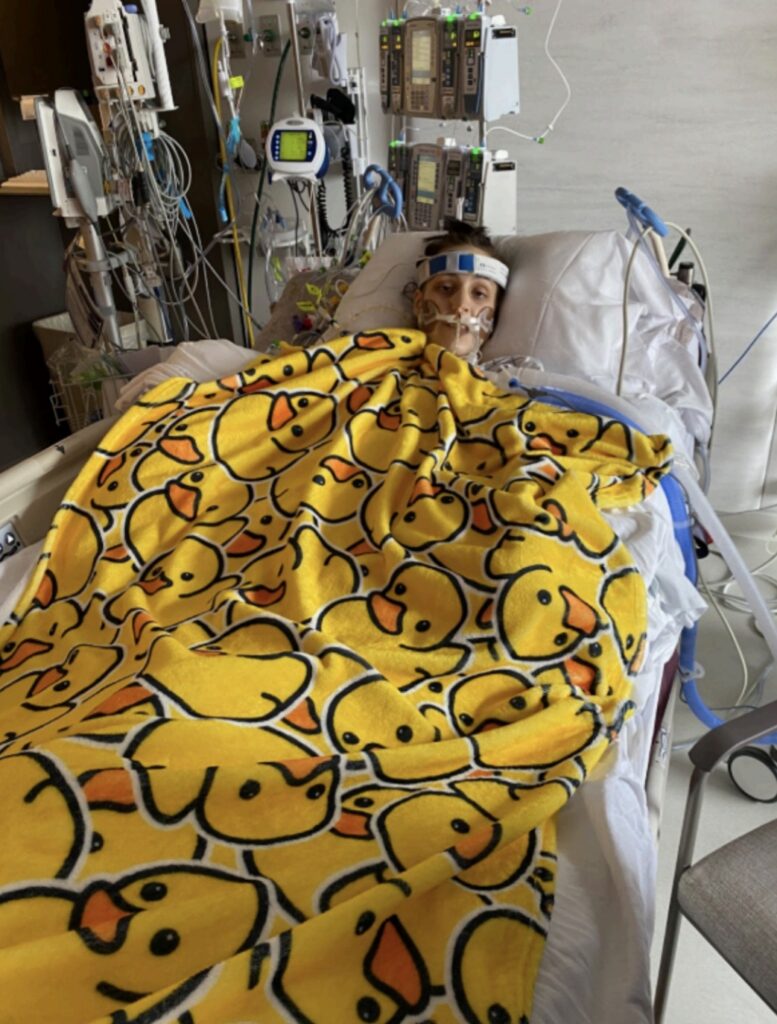
I was placed on the transplant list as Status 1A to try to get a heart for me as soon as possible. In the two weeks of waiting for my transplant, I was placed on a ventilator because my lungs were filling with fluid. I was dying, and I was dying quickly. I had also sustained a spinal stroke while waiting for my transplant. Finally, I received my heart on March 21, 2022. I remember being rolled into the OR, barely conscious, and being asked, “Do you have any questions before we start?” I asked the transplant surgeon if I was going to die. I don’t remember his answer, only his calm kindness.
When I was a kid, I was kind of shy, more of a quiet observer type. It wasn’t that I never had anything to say; it was that I was afraid of how I would be perceived. I never really knew what I should say. I kept my words safe inside of me for most of my life. In the two days after my transplant surgery, I would not speak or write notes. The words were once again stuck inside of me, just as they were when I was a kid. I knew I wanted to say something; nothing could encapsulate what I was thinking.
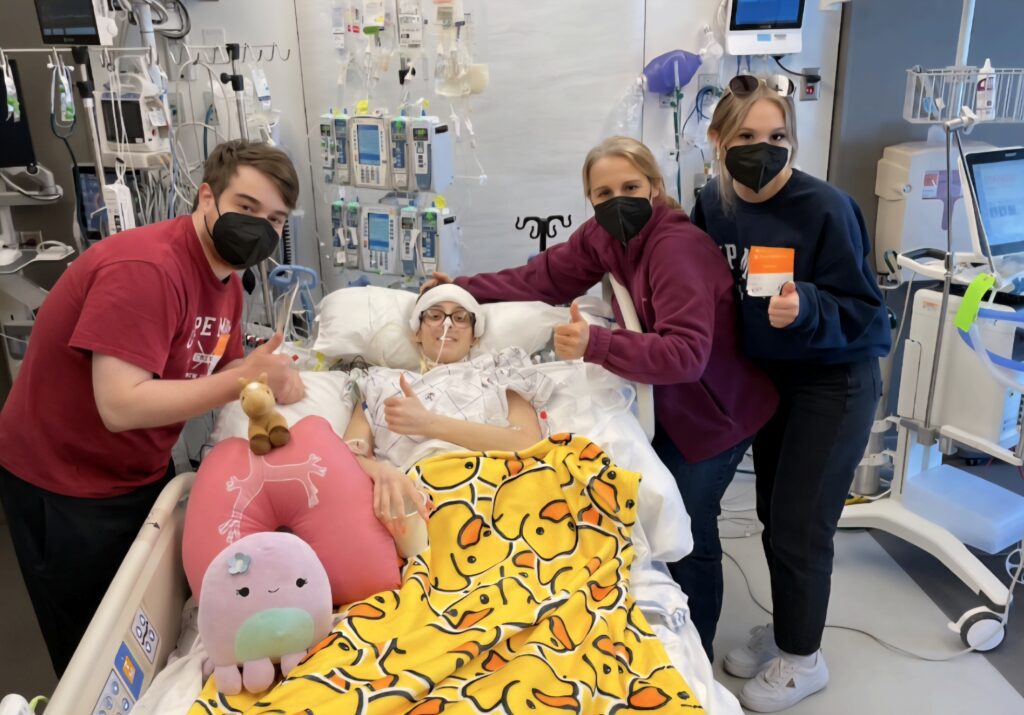
In the beginning months after my transplant, everyone told me I was lucky. But I was stuck at this strange intersection of not knowing the magnitude of what I survived, not knowing what it meant to be lucky, being so immensely thankful to be alive, and questioning why everything I thought I had planned for my life had been turned upside down.
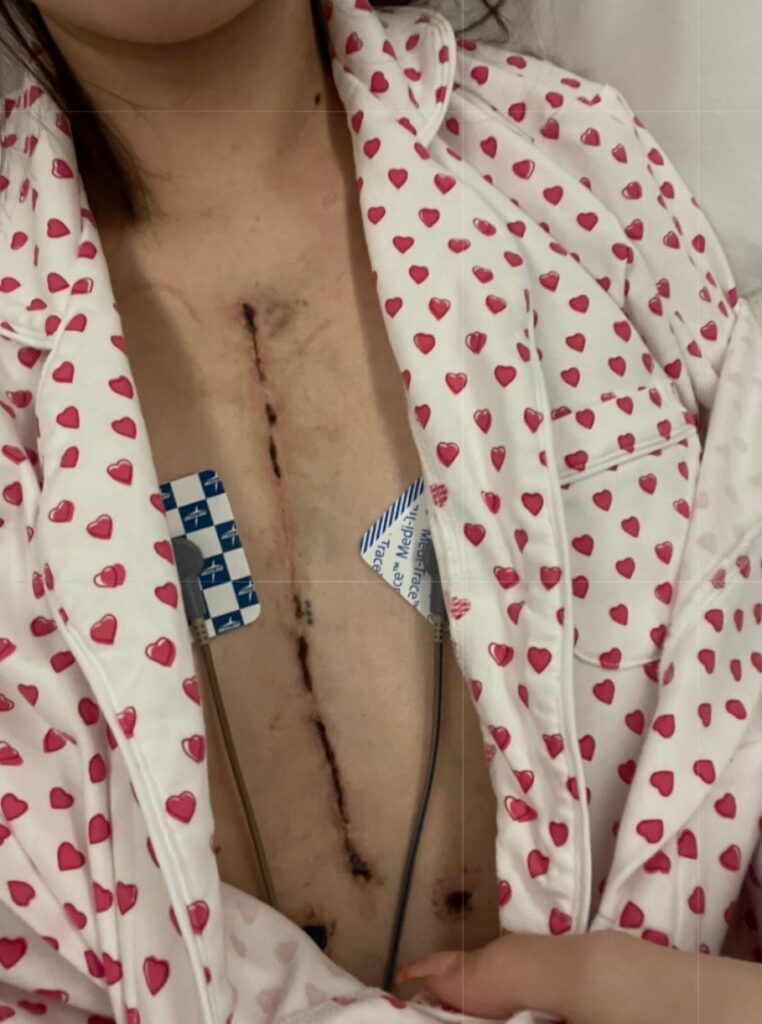
After being intubated for a while, my voice sounded foreign to me. I have never been a good or strong singer, but my hum became breathless.
My laugh had always been loud and sometimes obnoxious, but when it fell silent, I quickly realized I missed it more than anything. I had a new body that I didn’t recognize and a new rough idea of a life plan that did not yet feel like my own. There was one night, soon after coming home from rehab, when I was taking my vast number of nightly pills, and I broke down crying.
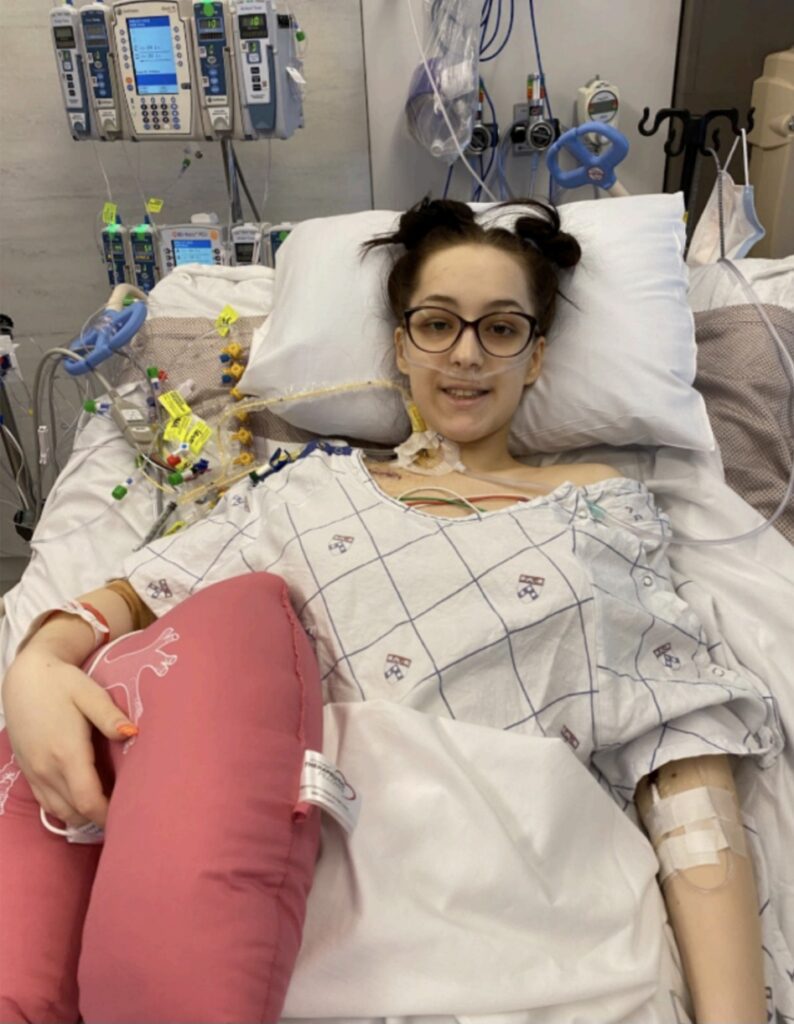
My family looked at me like I was crazy at first; I think they were trying to understand how the feeling of luckiness could be overpowered by another, more complicated feeling—grief. As someone who always loved the freedom of no structure, I felt so exhausted by having to follow this new, strict routine.

I had this deep feeling in my soul that every cell of my being had changed—that I would never walk again, that I would never just go back to who I was before. It posed a new question: What if I was always meant to end up this way? What if I was meant to have a new laugh and voice, a new perspective, a new body, a new future?
What if this would teach me how to say all of the things I feared saying for my entire life? What if it is actually better that I cannot go back to who I was before? I did not want it all to mean that what happened to me was cruel or unfair. I desperately wanted to shake hands with my grief, call it a truce, and somehow live in peace with its shadow so that it would not dim my life forever.

I began unpacking everything that transpired leading up to my transplant. I wanted to take it all apart piece by piece to inspect it, to try to understand the luckiness that found me. My sister had taken detailed notes throughout my arrival at the hospital, all the way until the week after my transplant surgery. She and my mother saved all the notes I wrote while on a ventilator, when my writing was barely legible at times. I vividly remember being frustrated while writing each one because the words never came out the way I wanted.

From all the pain and sleep medications I was on, I didn’t know how to write normally—some letters and words were so tiny or squished together that they made no sense. I read them so many times that the memories etched themselves into me. Reading that your family was told to make death plans for you if a heart didn’t rescue you in a few days is something you can never forget.
The memories of the ICU tug at me sometimes, and I often can’t tell if it is from the fear that some imaginary clock is ticking against me or if it is because I feel I haven’t thanked that room enough. It can freeze me for moments in time, holding me hostage. I wake in the middle of the night after having dreams of memories I try to suppress in my waking life—the ones that are too staggering to face.
Though there is something else I read in my sister’s notes, which she wrote the day after my transplant surgery, that has not left me either: “I’m sitting in the chair in the sky lounge and don’t have to sit and wonder if Carrots will get a heart or not.” If for no grander reason than living another day where my sister calls me Carrots, living another year where my mother squeezes my hand during quarterly bloodwork tests, or laughing my new laugh with my best friends, I think it is still worth it.
As I write this, the geese are loudly migrating over the Lehigh Valley in Pennsylvania, where I live. I wonder if they are flying back to places they feel they did not thank enough—if they are driven by their memories too. I think about the woman who saved my life. I tell everyone about her, even strangers. I tell them how she is the ink of my name when I dot the “i” in Caroline with a heart. How I carry her like a second soul. How she finds me in every poem I write at 2 a.m. I wonder a lot about my lucky Penny—if her spirit returns to those thankful places, to the creek or grass barefoot.

If she could be out there on the clouds the geese are flying under, arms outstretched in fields of cotton sky. If she had a clear view of the last full Blood Moon in March 2025 and thought that it looked like the magnificent heart, she gifted me.
Most days, I wake up with the sun shining in my eyes, and occasionally I wish my blinds would close tighter, but I am reminded of a random quote I read online: “I opened two gifts this morning; they were my eyes.” I believe the third gift is my heart, beating with me, no matter the fear that creeps in or the memories that feel like a confusing illusion. I say that I am lucky, and I feel that I am.

Caregiving. Most of the time, this word conjures images of grown children caring for aging parents, or seniors caring for seniors. Sometimes it brings to mind younger people caring for a loved one with cancer. One image most people don’t consider is caregivers for chronic conditions. We are unsung heroes.
It comes with mixed feelings. Our loved ones are dying… but slowly. Some can even be restored to “normal” with a transplant, if everything goes well. Others move through stages, gradual or abrupt, that require constant adjustment and flexibility. The traditional definition of a caregiver doesn’t always apply. In conversations, we may feel guilty about identifying as caregivers. But our role is long, arduous, and often misunderstood.
We are caregivers.

We navigate care. We become armchair experts, hyper-attuned to any nuanced change in our loved one. We move through endless lists of specialists. We get listed for transplant at this hospital, or that hospital — sometimes five different ones. We become disciplined and relentless in medication management, movement, emotional regulation, and advocacy. We live constantly on the razor’s edge between compassion and militancy to keep our person alive and thriving.
We are caregivers.
We need support, love, inclusion, respite, and care of ourselves. We deserve recognition for the work we do — even if we don’t seek it. We deserve community and safe spaces to connect with others, to talk or not talk about our experiences, and to remember what it feels like to be a full human being independent of caregiving.
I urge you to find spaces like this for yourself, so you can continue the fight.
Because:
WE ARE CAREGIVERS.

August 22, 2022, changed my life. My now-fiancé and I had only been dating for two and a half months when he was diagnosed with end-stage renal failure. To say our lives were turned upside down is an understatement. We were still learning about each other when we suddenly found ourselves facing kidney failure — he as the patient, and I as the caregiver.
Coming from a background of service as a Veteran, it was a no-brainer that I would tackle this journey head-on. And oh, what a journey it has been — a rollercoaster of emotions, triumphs, and setbacks all at once.
In the early stages of a relationship, every day usually brings new discoveries, laughter, and sometimes awkward moments. For us, those moments were suddenly magnified by a medical crisis. We were no longer just exploring favorite foods or binge-worthy shows; we were navigating lab results, dialysis schedules, and endless doctor appointments.
My military background instilled in me a deep sense of duty, discipline, and service. But nothing could have prepared me for the emotional intensity of watching someone I love fight for his life. Overnight, I became his advocate, nurse, nutritionist, and emotional anchor. There were days when the weight of responsibility felt overwhelming, and nights when fear crept in uninvited.
Being a caregiver means embracing a whirlwind of emotions: grieving for the life we once imagined, hoping for better days, feeling frustrated by setbacks, and holding profound gratitude for even the smallest victories. This journey has revealed depths of empathy and love I never knew I possessed. We have grown together in ways I never could have imagined, finding joy in quiet moments and celebrating every step forward.

Our story is not one of perfection, but of perseverance and partnership. Every challenge has been a lesson. Every triumph has been a reason to hold each other closer.
If you are reading this as a fellow caregiver, know that you are not alone. Your strength and compassion matter, even on the hardest days. Remember to care for yourself as fiercely as you care for your loved one. As difficult as it may be, this is the number one rule.
The journey will always be unpredictable, but your courage lights the way.
Thank you for joining me as I continue to share our story — one day, one triumph, and one setback at a time. I currently reside in California and have included both local and national caregiver resources.
National and Online Caregiver Resources
- Family Caregiver Alliance
- In-depth information, personalized support, CareNav dashboard, and resources in multiple languages.
- Family Caregiver Alliancecaregiver
- Caregiver Action Network
- Free education, peer support, and resources for family caregivers, including a Caregiver Help Desk and condition-specific guides.
- Caregiver Action Networkcaregiveraction
- National Institute on Aging – Caregiving Toolkit
- Evidence-based articles, infographics, publications, and videos for caregivers.
- NIA Caregiving Toolkitnih
- AARP Caregiving Support Groups
- Guidance on finding the right support group, both online and in-person, with tips for connecting with others who understand your journey.
- AARP Caregiving Support Groupsaarp
- Family Caregivers Online
- Articles, webinars, support groups, and a resource directory for caregivers nationwide.
- Family Caregivers Onlinefamilycaregiversonline
- VA Caregiver Support Program
- Specialized support for caregivers of veterans, including counseling, education, and financial planning.
- VA Caregiver Support Programva
- Comprehensive List of Support Groups
- A roundup of 22 online and in-person caregiver support groups, including those for specific conditions.
- 22 Remarkable Caregiver Support Groupsseniors

My name is Sam and I’m an extremely lucky, completely blessed, and eternally grateful heart recipient and survivor since April 2015. Like most organ recipients, I too hadn’t imagined ever needing a transplant but now, almost 11 years post-transplant, I’m not just surviving, but thriving. My first-hand experiences have allowed me to listen, observe, and become well-educated about all things Organ Donation and Transplantation over the years. I’ve become a fierce advocate/voice for transplant patients/recipients and others who may be connected to transplantation, both as an individual contributor and through other advocacy entities/organizations. I’m not an expert in this arena by any means, but I try to be aware, diligent, and be well-informed about things going on in this ever-evolving space.
I feel it’s important for all of us in the larger transplant community to be involved and invested in our collective care, which is why in upcoming newsletters, I plan on providing information about relevant media stories, advocacy efforts, and proposed legislation.
If anyone has relevant items/information to share, your content could possibly be featured in this section of the newsletter! Kindly contact me by sending a direct message to my profile on TransplantLyfe. Alternatively, please don’t hesitate to email me at sam@transplantlyfe.com.
——
At present, in the United States, there are over 90,000 people waiting to receive a life-saving kidney transplant. The demand for kidneys far exceeds the supply, leading to long waits, sometimes more than 5 years. Over the years, there have been some policy changes and efforts to improve data, equity, and transplant rates. However, the waitlist continues to grow because not enough folks are able to be transplanted due to the shortage of organs. Additionally, there’s been a troubling decline in deceased donor transplants in the last 12 months. Consequently, the need for more donors is even more critical. One viable solution to increase the donor pool is to encourage more living donors to step forward and donate a kidney to save a life. To that end, there has been some great work to introduce legislation that could help mitigate the organ shortage situation.

One such proposed legislation is the (EKDA) End Kidney Deaths Act (H.R. 2687) which is a ten-year pilot program that will provide a refundable tax credit of $10,000 each year (for a total of $50,000 over 5 years) to living kidney donors who donate a kidney to save the life of a stranger, by way of a non-directed donation. A non-directed kidney donor is someone who donates without having a specific recipient in mind when donating a kidney. This one selfless act could even start a “chain” of transplants which would potentially help several recipients. These non-directed kidneys will go to those on the National Waiting List who have been listed for the longest. The hope is that by the 10th year after the passage of the EKDA, up to 100,000 Americans who had been suffering on the waitlist will instead have healthy kidneys. (Also, over this period of time, taxpayers will have saved several billions too.)
To learn more information about EKDA, you can visit its Congress.gov listing, and/or https://www.endkidneydeathsact.org/., and watch this educational video. Interested advocates can also sign this petition.
#Advocacymatters #PatientVoice #livingdonorssavelives #shareyourspare #beanorgandonor #bealivingdonorhero

Twelve years after my kidney transplant, it’s impossible to ignore both the freedom it’s given me but also one of its most serious challenges: skin cancer. With a family history of cancer and lifelong immunosuppression, I knew the risk was real.
After an initial diagnosis in 2021 and back-to-back diagnoses in late 2025/early 2026, I felt compelled to share my journey with biopsies, Mohs surgeries, and wound complications so others can benefit from my experiences.
Ultimately, here’s what I learned:
Stay vigilant about checking your body. Trust your gut. Don’t ever settle for appointments that seem eons away. While skin cancer is a common transplant experience, it’s valid to express displeasure if it happens to you. It may happen again. You can complain that time too. Your gratitude for a life-saving transplant is in no way diminished by being angry (or frustrated) you may have to endure skin surgeries, physical pain, stress, and medical bills. You’re not alone. The TransplantLyfe community is here for you.
This is my story…
——
Recently, when driving back home from an evening concert in New York City, I reflected on my health and all the gifts my kidney transplant has afforded me in the almost twelve years since my surgery.
The ability to enjoy a night out with friends, experiencing my favorite pastimes (live music) without having to worry about rushing home early to plug into a peritoneal dialysis cycler for 10 hours, is certainly at the top of that gratitude list.
However, the following morning, in stark contrast to the previous night’s fun, I woke up very early for a not-so-pleasant aspect of transplant life: addressing skin cancer (again).
I’m currently 39 years old and my first experience with the dreaded “c”-word occurred in middle school when my father required invasive surgery to remove a melanoma on his arm. At the time, there was concern it had spread to his lymph nodes. Thankfully, the tumor was fully excised and Dad was OK. In the years since, he faced numerous instances of skin cancer, many of which involved Moh’s Surgery to resolve. (More on this highly effective removal technique later.)
When I received my living donor transplant from a close friend in 2014, I was told about the heightened risk of skin cancer due to the immunosuppressive drugs I would be taking for life. When factoring in family history, skin vigilance had to become an important part of my overall routine. Hats and high-SPF sunscreen became staples of my summer. I started seeing a dermatologist once a year for full-body screenings and tried my best to keep mental track of anything on my body that seemed off. Occasionally, some skin lesions such as actinic keratoses were frozen or burnt off just to be safe and to ensure these pre-cancerous conditions didn’t evolve.
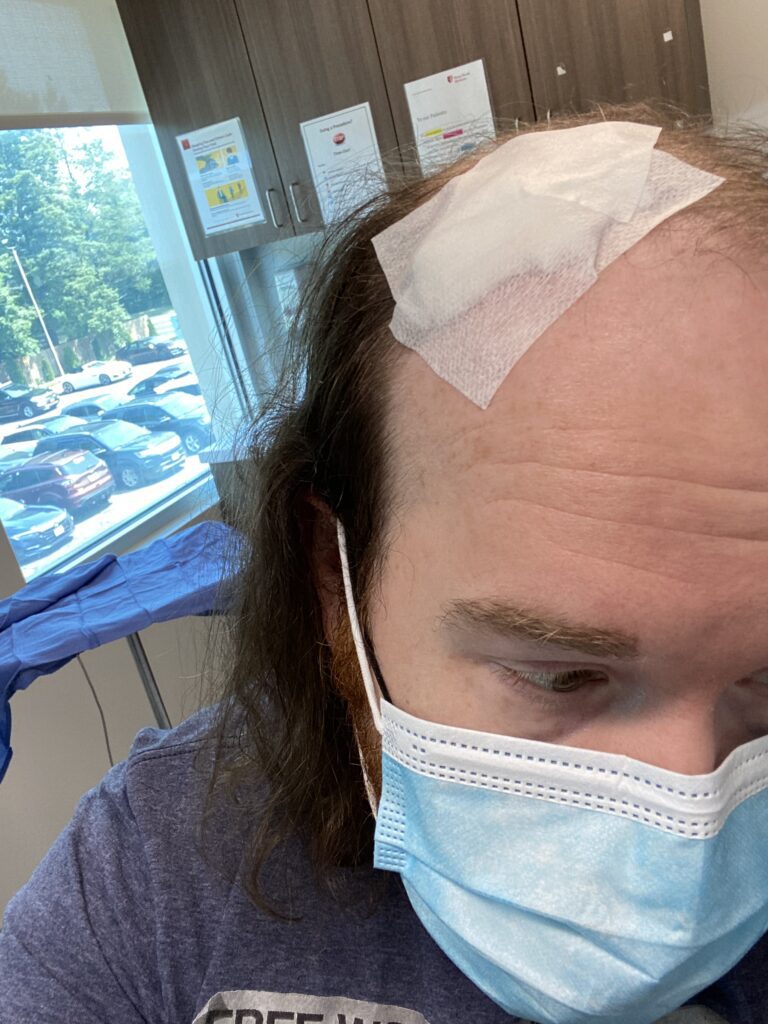
In May of 2021, 7 years post-transplant, I noticed a small, dime-sized mark on the front of my hairline. Initially thinking it was just dry skin, I applied cream and observed it over the course of a few days. Nothing changed and my gut felt that something was wrong. I called my dermatologist who unfortunately was booked out about 8 weeks. I took the next available appointment on June 28th, we biopsied the spot via a tiny surgical cut, and on July 4th weekend I received a call noting the sample was a basal cell carcinoma. My first-ever Moh’s Surgery was scheduled for the next morning, and I was told to bring a book or something to occupy my time as the procedure could take upwards of 3 hours.
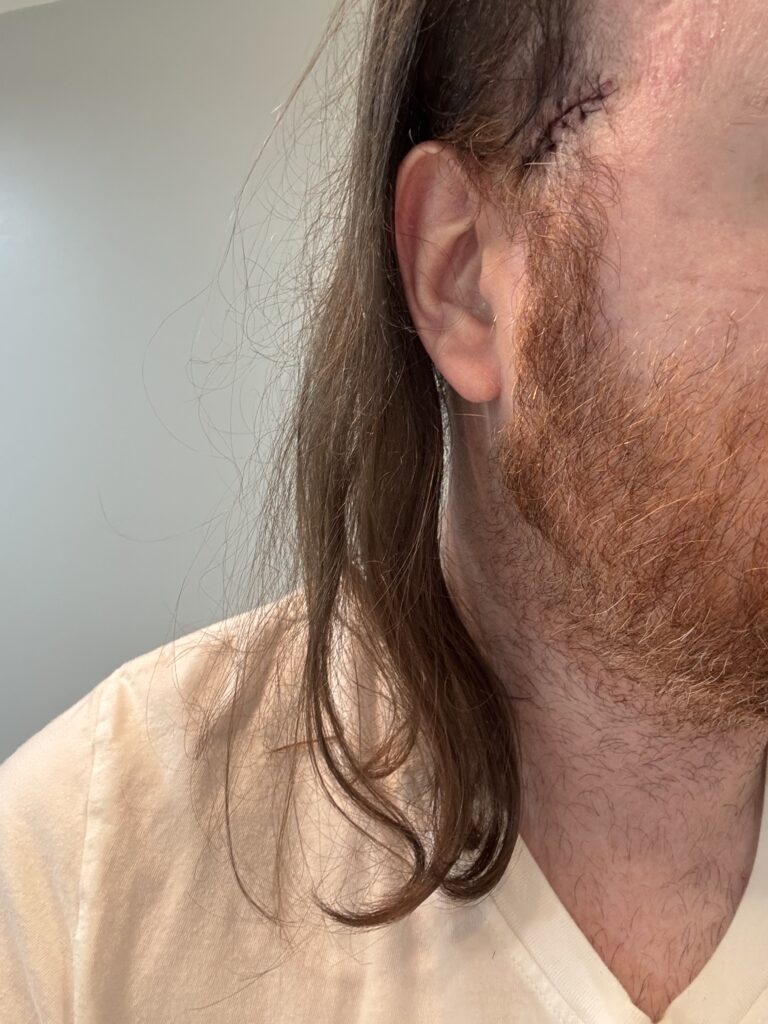
Moh’s Surgery involves numbing the area with local anesthesia followed by extremely precise surgical removal of tissue, which is then viewed under a microscope to detect cancer cells along the edges. No cancer cells, no more surgery. If cells are present at the edges, it’s time for more cutting. The wound is commonly sutured closed or cosmetically restructured using skin grafts or synthetic skin substitutes, depending on the location and size of the gap. Moh’s is highly effective for skin cancer, with success rates as high as 99% according to Johns Hopkins Medicine.
While I was very grateful the cancer was gone, I was still annoyed it took me weeks to get a proper office visit. After doing some online research, I found another clinic, which was highly rated, took my insurance, and even offered night hours and same-day appointments. I never returned to my prior provider.
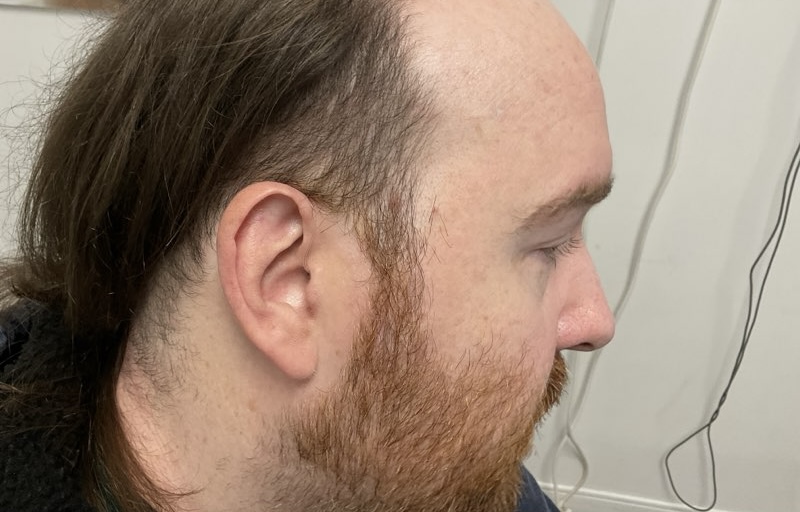
Fast forward to the Fall of 2025, when I noticed a small tan colored spot just above my sideburn. My current dermatologist had me come in right away; the spot was frozen, and a few weeks later, it was out of sight and mind. Until it wasn’t. By December, the spot began crusting again and a biopsy confirmed the presence of a basal cell. I opted for Moh’s right away, pre-holidays. I forgot how much the local anesthesia needles hurt when entering the skin. I was quickly reminded of how the fresh incision felt a few hours later once the meds wore off. The sutures on the side of my head were TIGHT and sleeping was very uncomfortable. On New Year’s Eve, we removed the sutures, closing the door on that situation, and randomly biopsied a bleeding spot on my leg, which I initially thought was a minor cut.
The first week in January 2026, I had a voicemail from the dermatologist about “the results” from my leg. Since they didn’t leave good news on my line, I assumed the obvious: more cancer. Sometimes I hate it when I’m right.
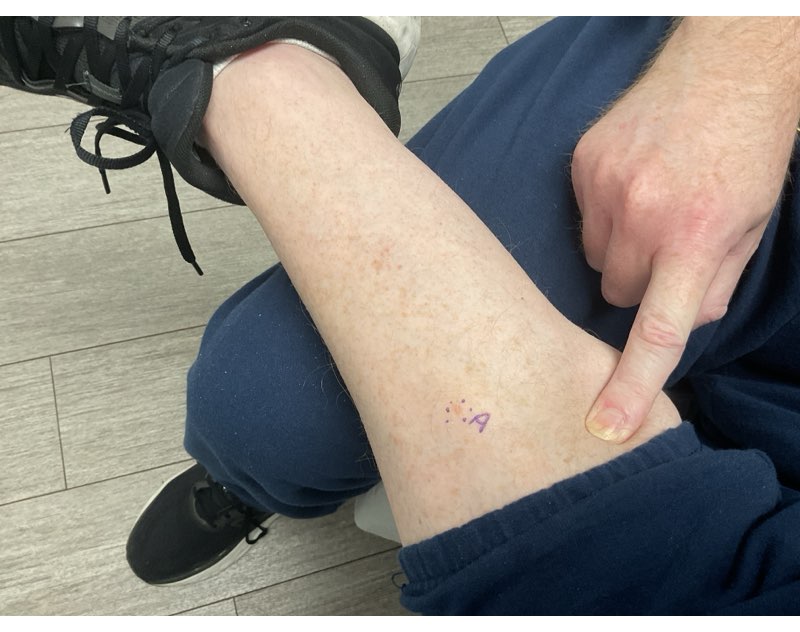
The leg biopsy site wasn’t healing well, likely due to me being immunocompromised, but after a few days of topical creams, on January 15th, I had Moh’s for the second time in under a month. This spot was on the shin of my left leg. Same painful needles, same rude awakening hours later when the numbing meds wore off. Sleeping was OK but standing up and feeling the blood flow to the wound was OUCH.

On January 18th, still reeling from the pain in my leg, I woke up to tons of blood on my pillow. Despite my head sutures having been removed weeks prior, the center of the wound reopened exposing a gaping hole. This is known as wound dehiscence. It can happen even with a perfect suture job due to a multitude of factors. Thankfully, no infection was present.
On January 19th, the wound was re-sutured, and I was back to bandages and the TIGHT pain. We agreed to leave these stitches in longer than usual and will do the same with my shin sutures.
While more cancer in my future is uncertain, all I know for sure is that I will be going to another concert next week.